

Heart problems are often associated with blocked arteries and heart attacks. Heart valve disease receives far less attention, even though it can gradually affect how efficiently the heart pumps blood around the body.
Part of the problem is that its early signs can be easy to dismiss. Breathlessness when climbing stairs, feeling unusually tired or noticing that you cannot exercise as comfortably as before may be written off as ageing, stress or simply being unfit.
Yet these can also be signs that one of the heart’s valves is no longer working properly.
As Singapore’s population ages, heart valve disease is becoming an increasingly important clinical issue, says Dr Loh Yee Jim, Senior Cardiothoracic Surgeon at Mount Elizabeth Novena Hospital and President of the Chapter of Cardiothoracic Surgeons, Academy of Medicine, Singapore.
At the same time, treatment itself is changing. Rather than looking at heart valve surgery as a single procedure that solves an immediate problem, doctors are increasingly considering what may happen to a patient 10, 20 or even 30 years later.
This approach is sometimes described as lifetime valve management.
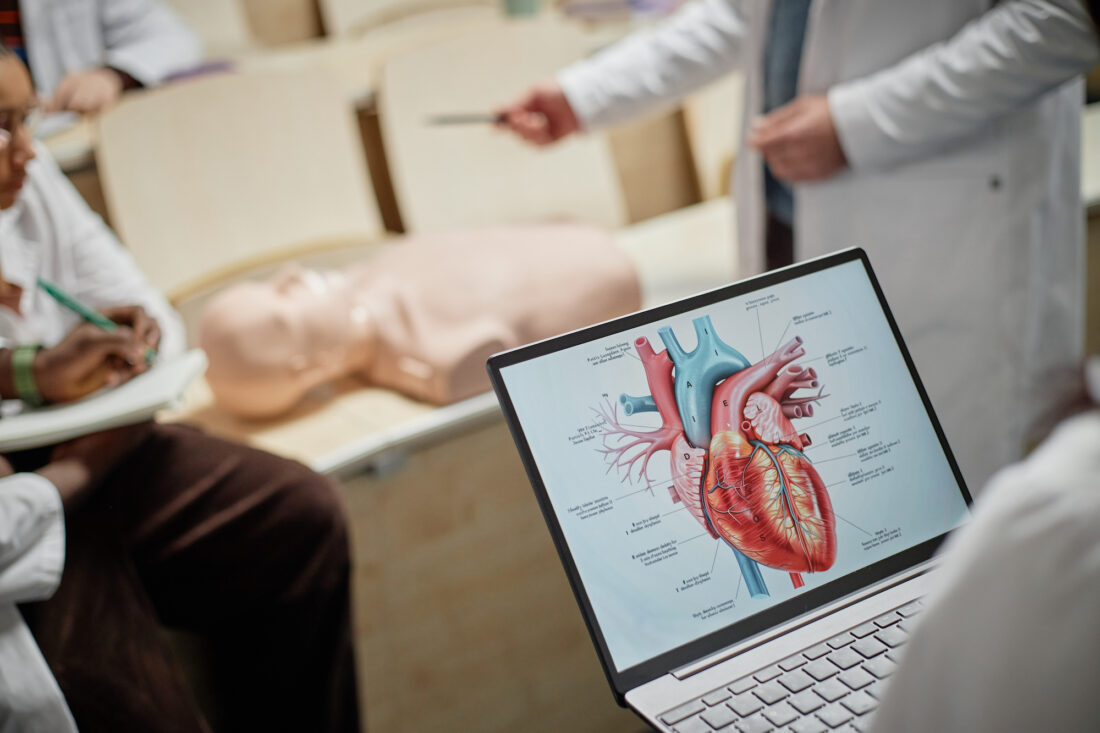
What happens when a heart valve stops working properly?
The heart has four valves — the aortic, mitral, tricuspid and pulmonary valves — which help keep blood moving in the correct direction.
Heart valve disease generally develops in one of two ways.
With stenosis, a valve becomes thickened, stiff or calcified, narrowing the opening through which blood needs to pass. The heart then has to work harder to pump blood through it.
With regurgitation, sometimes called a leaky valve, the valve does not close properly and blood flows backwards rather than continuing efficiently through the heart.
Older adults are more likely to experience degenerative conditions such as calcific aortic stenosis or mitral valve prolapse, but valve disease is not exclusively a condition of old age.
Younger people can also be affected by congenital abnormalities such as a bicuspid aortic valve, where someone is born with two valve leaflets instead of the usual three, or by valve damage associated with conditions such as rheumatic heart disease.

The symptoms are easy to overlook
Heart valve disease may develop slowly enough that a person adjusts to the changes without realising it.
Someone who used to walk quickly up a flight of stairs might start taking the lift more often. They might stop exercising because they feel unusually tired, or assume that breathlessness simply comes with getting older.
Symptoms worth paying attention to include:
- unusual shortness of breath during everyday activity
- persistent or unexplained fatigue
- chest tightness or discomfort, particularly during exertion
- swelling around the ankles, feet or abdomen
- heart palpitations or an irregular heartbeat.
Dr Loh cautions against automatically attributing a decline in physical capacity to age. A doctor may first detect an abnormal heart sound or murmur using a stethoscope, with an echocardiogram then used to examine the heart’s structure and how well its valves are functioning.
Why doctors are thinking beyond the first operation
Traditionally, conversations around heart valve treatment tended to focus on solving the immediate problem. That approach is evolving.
“Lifetime valve management” means considering how the first treatment decision might influence the options available if the patient needs further treatment many years later.
For someone diagnosed relatively young, that matters because one procedure may not necessarily be the last intervention they require during their lifetime.
Dr Loh describes this as moving away from treating surgery as a “one-and-done” event towards planning several possible interventions over decades.
The principle is relatively simple: the treatment that works best today should ideally leave useful options open for tomorrow.
That does not mean every patient will undergo several procedures. It means surgeons increasingly consider future possibilities when recommending what should happen first.
Heart valve surgery has changed considerably
The treatment landscape has expanded over the past decade.
Open-heart surgery remains an important option and may still be the safest treatment for some patients. But surgeons and cardiologists now also have minimally invasive and catheter-based procedures available in suitable cases.
These include transcatheter aortic valve replacement (TAVR), where a replacement valve can be delivered through a blood vessel rather than through conventional open-heart surgery, as well as catheter-based approaches for some mitral valve conditions.
Imaging has also improved. Three-dimensional echocardiography, detailed CT scans and computer-based procedural modelling can give clinicians a much clearer picture of an individual’s heart anatomy before deciding how to proceed.
The result is a more personalised approach to treatment rather than choosing a procedure based on age alone.
There is no single ‘best’ heart valve
For people who require valve replacement, one of the major decisions can be whether to use a mechanical valve or a bioprosthetic, or tissue, valve.
Mechanical valves are made from highly durable synthetic materials and are designed to last for a very long time. However, patients generally need lifelong anticoagulant medication and regular monitoring because of the risk of blood clots.
Tissue valves are made from biological tissue. They generally do not require lifelong anticoagulation solely because of the valve, although they may eventually deteriorate and need further treatment.
That is why the choice is not simply a question of which valve lasts longest.
Doctors also consider factors such as a person’s age, physical activity, occupation, existing medical conditions, bleeding risk and anatomy.
Lifestyle matters too. Someone who participates in contact sports, travels frequently, plans to become pregnant or has difficulty managing regular medication may have different priorities from another patient.
Even someone’s home circumstances can be relevant. Dr Loh notes that caregiver support and a person’s ability to manage medicines safely can influence treatment decisions.
Newer tissue valves are changing the conversation
Historically, younger patients in particular faced a difficult trade-off.
A mechanical valve offered durability but came with lifelong anticoagulation. A tissue valve often provided greater lifestyle flexibility but might deteriorate sooner, potentially leading to another operation.
Newer tissue treatments are intended to delay this deterioration.
One example is RESILIA tissue, developed by Edwards Lifesciences, which uses an anti-calcification treatment designed to reduce the calcium deposits associated with structural valve deterioration.
Dr Loh pointed to 10-year findings from the COMMENCE study, which reported close to 98% freedom from structural valve deterioration at 10 years among study participants.
While long-term data can help doctors and patients make decisions, no valve or procedure is universally suitable. Age, anatomy, existing illnesses and individual priorities still need to be considered with a cardiac specialist.
A second procedure may not mean another open-heart operation
The prospect of needing another operation understandably worries many patients. Lifetime planning is partly intended to make future treatment less daunting.
Some modern surgical bioprosthetic valves are designed with future catheter-based procedures in mind. If a tissue valve deteriorates years later, suitable patients may be able to undergo a valve-in-valve procedure, in which a new transcatheter valve is placed inside the existing surgical valve via a blood vessel, rather than undergoing another open-heart operation.
Whether this is possible depends on the patient’s anatomy, the original valve and their health at the time, which is another reason why surgeons increasingly consider future treatment options when planning the first procedure.

Heart valve disease is not the same as coronary artery disease
One misconception Dr Loh frequently encounters is that heart valve disease and coronary artery disease are essentially the same condition.
They are not. Coronary artery disease affects the blood vessels supplying the heart, while valve disease affects the structures controlling blood flow through the heart. Symptoms such as breathlessness and chest discomfort can overlap, however, which is why medical assessment is important.
Another misconception is that older people are automatically too frail for treatment. Chronological age alone does not determine whether someone is suitable for an intervention. Doctors assess the individual’s overall health, anatomy, risks and expected benefits.
Nor does valve surgery necessarily mean giving up an active life. Treatment is intended to improve heart function and, where possible, help patients return to everyday activities, work, travel and exercise.
Looking after your heart — and your teeth
Not every form of heart valve disease can be prevented, but managing cardiovascular risk factors still matters.
Dr Loh recommends keeping hypertension, blood glucose and cholesterol under control. Elevated blood pressure, for example, places additional strain on the heart and its valves.
One less obvious factor is oral health.
Bacteria associated with severe gum infections can enter the bloodstream and, in some circumstances, infect the heart valves, causing a serious condition known as infective endocarditis. Good dental hygiene therefore forms part of protecting cardiovascular health.
Routine medical examinations can also help. Early valve disease may not produce obvious symptoms, but a doctor may hear a heart murmur during a standard examination and recommend an echocardiogram for further investigation.
Don’t assume breathlessness is simply part of ageing
Perhaps the most useful takeaway is also the simplest: pay attention when your physical capacity changes.
Persistent breathlessness, unexplained fatigue or a noticeable decline in what you can comfortably do should not automatically be dismissed as getting older.
Heart valve treatment has expanded considerably, and decisions are increasingly made not simply around getting a patient through one procedure, but around preserving health, lifestyle and future treatment options over many years.
As Dr Loh puts it, timely assessment can turn what initially feels like a daunting diagnosis into a clearer long-term treatment pathway.
This article is for general educational purposes and does not replace personalised medical advice. Treatment options for heart valve disease vary according to an individual’s condition, anatomy and overall health. Speak with a qualified healthcare professional about your own circumstances.
Images: Envato


 Melissa Fann


 Trevor Klass
 Guest Contributor





